Kidney problems can worsen quietly, while a sudden change in urine output, breathing, blood pressure or mental alertness can signal an urgent complication. You will learn which symptoms need emergency care, which tests reveal early kidney damage, how to reduce avoidable risks, and when nephrology, urology or primary care is the right next step.
Key takeaways
- Seek emergency care for very low urine output, breathlessness, confusion, or severe flank pain with fever.
- Check eGFR alongside urine albumin to assess kidney risk more accurately.
- Review medicines, dehydration, infections, blood pressure, and lifestyle factors that can strain kidney function.
- Bring test results, medication details, and symptom changes to your nephrology appointment.
Know When Kidney Symptoms Need Urgent Attention
Emergency care is needed for very low urine output, breathlessness from fluid overload or possible kidney complications, confusion, unusual drowsiness, severe flank pain with fever, or sudden blood-pressure elevation with headache, chest pain, weakness or vision changes. Do not wait for a routine appointment.
| Urgency | Symptoms and action |
|---|---|
| Emergency department now | Very low urine output with breathlessness, confusion, fainting, chest pain, severe weakness, or rapidly worsening swelling |
| Same-day nephrology or medical review | Blood in urine, new swelling around the eyes or ankles, persistent vomiting, a marked urine-output drop, severe flank pain, or sudden blood-pressure elevation without emergency features |
| Routine primary-care follow-up | Mild, stable ankle swelling or recurring urinary changes without pain, fever, vomiting, breathlessness or reduced urine output |
Visible blood in urine deserves same-day assessment even if you feel well. Clots, inability to pass urine, or blood with severe pain requires emergency care.
Acute kidney injury can develop after dehydration, infection, urinary blockage or a medication effect, and symptoms can be subtle or absent. A “not very high” creatinine does not rule out danger because creatinine can lag behind a rapid decline, especially with low muscle mass.
Clinicians compare your baseline and current results with urine output, potassium and other electrolytes, fluid status, medicines and possible obstruction. If symptoms settle, arrange follow-up testing rather than assuming the kidneys recovered.
Screen for Silent Damage and Read the First Results Correctly
Kidney screening belongs on your care plan if you have diabetes, hypertension, cardiovascular disease, obesity, recurrent kidney stones, repeated urinary infections, lupus, regular NSAID use, a family history of kidney failure, previous acute kidney injury, or known structural kidney disease. Kidney damage can advance without pain or urinary symptoms.
A first nephrology assessment usually includes:
- Blood-pressure measurement, including review of home readings and resistant hypertension
- Serum creatinine, estimated glomerular filtration rate and blood urea nitrogen
- Electrolytes and tests for acid-base problems
- Urine albumin-to-creatinine ratio and urinalysis for blood, protein and sediment abnormalities
- Review of medicines, illnesses, family history and fluid status
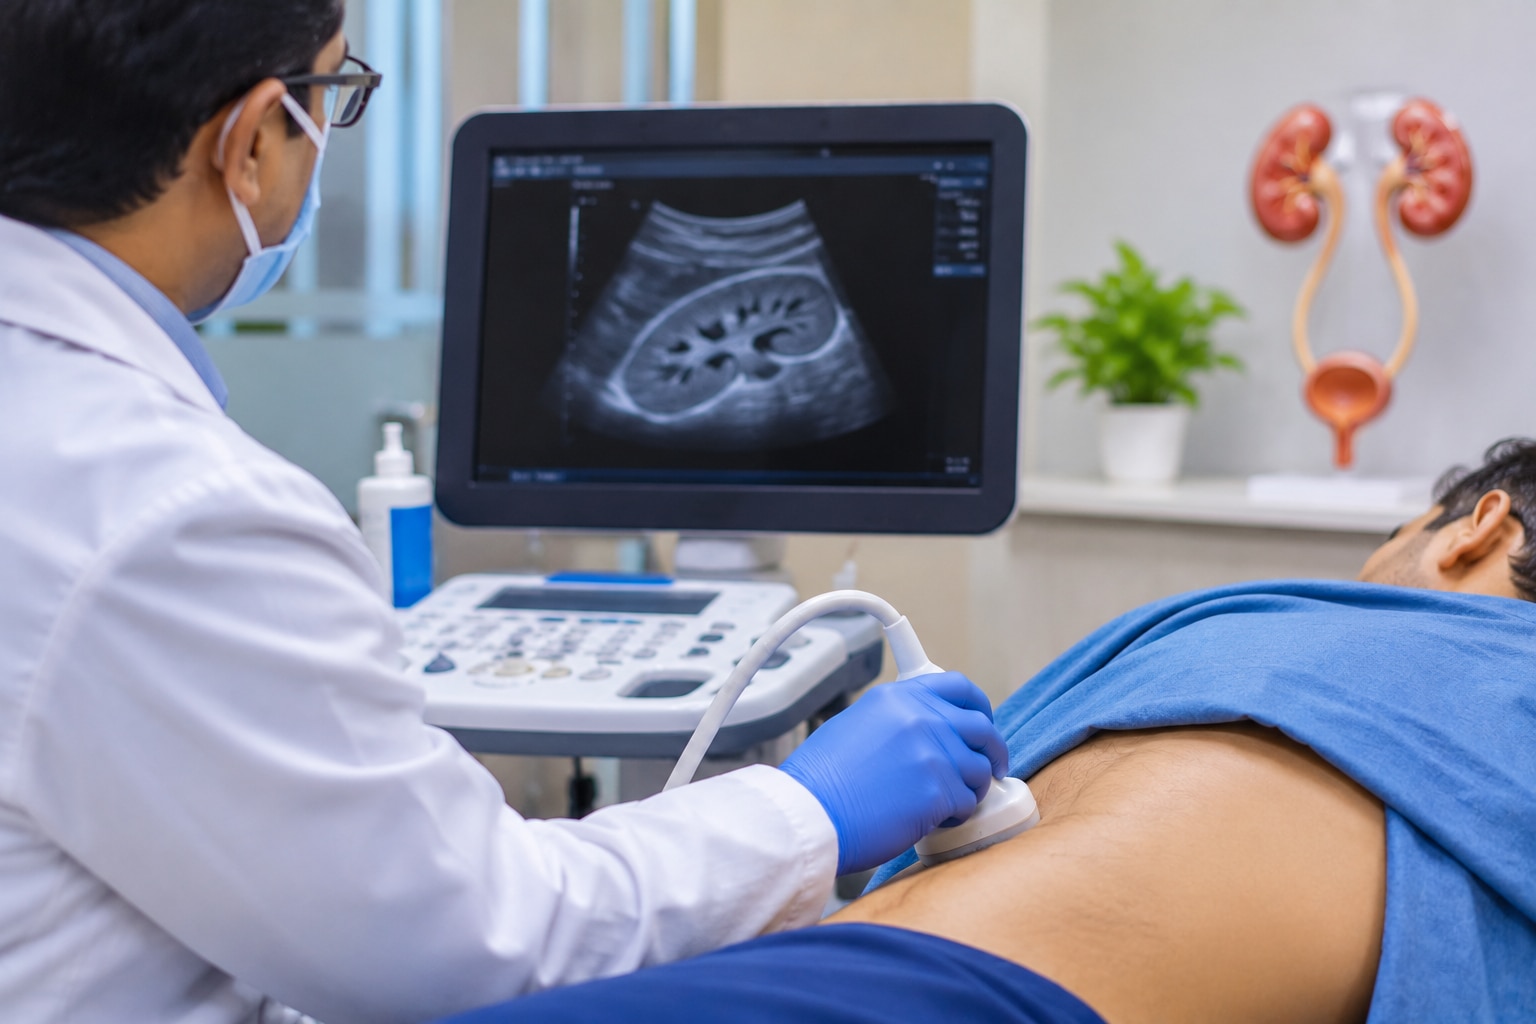
- Kidney ultrasound when obstruction, stones, structural disease or uneven kidney size is suspected
The clinician separates acute kidney injury from chronic kidney disease by checking previous results, recent illness, dehydration, medication changes and urinary obstruction. A sudden creatinine rise or fall in urine output points toward acute kidney injury; improvement after treating the trigger supports that conclusion.
Chronic kidney disease requires a kidney-function or structural abnormality lasting at least three months. An eGFR below 60 mL/min/1.73 m² for three months qualifies, while persistent albuminuria, abnormal urine sediment or imaging changes can establish chronic disease even with a higher eGFR. One abnormal report alone proves neither diagnosis.
Use eGFR and Urine Albumin Together, Not as Isolated Numbers
An abnormal serum creatinine result is a signal to investigate, not proof of chronic kidney disease. Creatinine varies with muscle mass, diet, hydration and medicines, while estimated glomerular filtration rate (eGFR) estimates filtration from creatinine and other factors. CKD requires a kidney abnormality lasting at least three months; one abnormal report cannot establish that.
Read the results together:
- eGFR below 60 mL/min/1.73 m² for three months supports CKD. A sudden fall can instead reflect acute kidney injury, dehydration, obstruction or a medication effect.
- Urine albumin-to-creatinine ratio (uACR) below 30 mg/g is A1, 30–300 mg/g is A2, and above 300 mg/g is A3. Persistent A2 or A3 albuminuria signals kidney and cardiovascular risk, even with a normal eGFR.
- Serum creatinine must be compared with your previous baseline. A “not very high” value can miss early or rapidly changing injury, especially with low muscle mass.
- Blood urea nitrogen and electrolytes add context about waste removal, fluid balance and complications. Clinicians also consider urine output, urinalysis, blood pressure, medicines and fluid status.
Repeat an unexpected eGFR or uACR after addressing acute illness, dehydration, fever, strenuous exercise or urinary infection. Persistent albuminuria, abnormal urine sediment, imaging changes or a kidney transplant history can indicate CKD even when eGFR is above 60.
Reduce Medication, Illness and Lifestyle Risks to Kidney Function
Protect kidney function by preventing dehydration, controlling blood pressure and diabetes, and avoiding unreviewed medicines. Drink regularly during heat, fever, diarrhoea or vomiting, and seek medical advice if you cannot keep fluids down or urine output falls.
| Risk | Why it matters | What to do |
|---|---|---|
| Ibuprofen, diclofenac, naproxen | These NSAIDs can reduce kidney blood flow and trigger acute kidney injury, especially with dehydration, diuretics or ACE inhibitors/ARBs. | Ask a clinician or pharmacist before regular or high-dose use. Check over-the-counter combination painkillers for hidden NSAIDs. |
| Prescription medicines | Diuretics, ACE inhibitors, ARBs and some antibiotics require monitoring during acute illness or after dose changes. | Do not stop them automatically; ask which medicines to pause, continue or test during vomiting, diarrhoea or fever. |
| Supplements and herbal products | High-dose creatine, vitamin C, bodybuilding products and imported herbal remedies can alter tests or injure kidneys. | Show the full label, dose and ingredients to your clinician before starting them. |
| Illness | Severe infection, dehydration, heart failure and urinary blockage can cause a rapid kidney decline. | Arrange prompt assessment for persistent vomiting, very low urine output, swelling or breathlessness. |
| Imaging procedures | Iodinated contrast for CT and, in advanced kidney disease, gadolinium for MRI require risk review. | Tell the imaging team your eGFR, kidney history and medicines before the scan. |
Use paracetamol only within the labelled dose unless a clinician gives different advice. Avoid crash diets and unregulated “detox” products.
Prepare for the Right Specialist and the Right Follow-Up
A nephrologist is the right referral for unexplained eGFR decline, albuminuria, electrolyte problems, resistant hypertension or suspected glomerular disease—not only dialysis. Choose a urologist for recurrent kidney stones, urinary blockage or repeated urinary infections; choose emergency care for very low urine output, breathlessness, confusion, persistent vomiting or severe flank pain.
Hinjawadi SuperSpeciality Hospital 08048033666 may be useful when urgent assessment and hospital-based follow-up need coordination.
| Option | Main job | Choose it when |
|---|---|---|
| Nephrologist | Kidney function, blood pressure and systemic kidney disease | Tests remain abnormal or the cause is unclear |
| Urologist | Drainage, stones and urinary-tract anatomy | Imaging shows obstruction or stones recur |
| Emergency physician | Immediate stabilisation and testing | Symptoms suggest acute kidney injury or dangerous complications |
| Renal dietitian | Food, fluid, sodium, potassium and protein planning | A clinician identifies CKD, electrolyte problems or dialysis needs |
1. Bring every medicine, supplement and NSAID painkiller, plus home blood-pressure readings, recent reports and a timeline of vomiting, infection, reduced urine or swelling. Ask whether you need serum creatinine, electrolytes, urine albumin-to-creatinine ratio, urinalysis or a kidney ultrasound.
2. Ask what would trigger admission: worsening kidney function, dangerous potassium or acid levels, fluid in the lungs, infection, obstruction or inability to keep fluids down. A biopsy is considered when tissue results could change treatment, such as suspected glomerular disease; it is not automatic.
3. Discuss kidney-replacement education before crisis care. Planning dialysis access, transplantation assessment or conservative kidney management becomes relevant around eGFR 15–20 mL/min/1.73 m² or a predicted two-year replacement risk above 40%; the eGFR alone does not decide when dialysis starts.
Frequently asked questions
Which kidney symptoms need urgent medical attention?
Seek emergency care for very low urine output, breathlessness from fluid overload, confusion, unusual drowsiness, severe flank pain with fever, or sudden blood-pressure elevation with headache, chest pain, weakness, or vision changes.
Why should eGFR and urine albumin be interpreted together?
eGFR describes how well the kidneys filter blood, while urine albumin shows leakage through the kidney filters. Using both results gives a clearer picture than relying on either number alone.
What can increase the risk of kidney-function decline?
Medicines, dehydration, acute illness, uncontrolled blood pressure, diabetes, and lifestyle factors can affect kidney function. Review these risks with a clinician rather than stopping prescribed medicines yourself.
How should you prepare for a nephrology appointment?
Bring recent blood and urine reports, a complete medicine and supplement list, home blood-pressure readings, and a record of symptoms, urine changes, illnesses, and questions.