Ear blockage, nasal congestion, sore throat, hoarseness, dizziness, and snoring do not all need the same treatment or the same clinician. You will learn how to sort common ENT symptoms, recognise emergencies, choose appropriate care, and prepare for testing or follow-up.
Key takeaways
- Do not use cotton buds for earwax; they can push wax deeper or injure the eardrum.
- Seek urgent assessment for sudden hearing loss, severe breathing difficulty, or uncontrolled bleeding.
- Persistent hoarseness, swallowing trouble, or repeated infections need specialist evaluation.
- Match ENT tests to your symptoms instead of repeating short treatments without a plan.
Which ear problems need ENT care, and which need urgent assessment?
"An earwax blockage usually causes fullness, reduced hearing, or ringing. Do not use cotton buds: they push wax deeper and can cut the ear canal or perforate the eardrum.
Cerumenolytic drops can soften wax when the eardrum is intact; manual removal or microsuction is safer when drops fail, a tube or perforation is present, or infection causes pain or discharge.\n\nSwimmer’s ear, also called otitis externa, affects the ear canal after moisture, scratching, or irritation; it is not a middle-ear infection.
Topical treatment is usually preferred.
A middle-ear infection or acute otitis media does not automatically require antibiotics: selected children with mild, non-severe symptoms can have 48–72 hours of observation with follow-up, while severe illness, ear discharge, or certain age and bilateral-disease patterns favour antibiotics.\n\n- Arrange ENT review for recurrent ear discharge, persistent ear pain, suspected eardrum perforation, tinnitus in one ear, or hearing loss that does not clear after wax removal.\n- Seek urgent assessment for hearing loss developing within 72 hours, because sudden sensorineural hearing loss needs prompt examination and audiometry; early corticosteroid treatment matters.\n- Seek emergency care for severe swelling behind the ear, facial weakness, uncontrolled pain, high fever with worsening illness, or a foreign object that cannot be removed safely.\n\nProblem | Safer next step | When to escalate\nEarwax blockage | Drops, manual removal, or microsuction | Avoid irrigation with perforation, tube, or active infection\nSwimmer’s ear | Keep the canal dry and obtain topical treatment | Review urgently if infection spreads beyond the canal\nTinnitus or hearing loss | Book examination and audiometry | Same-day assessment for sudden loss\nEar pain or discharge | Arrange otoscopy | ENT review when recurrent or persistent"
How should common nose problems be managed and investigated?
Allergic rhinitis causes sneezing, itching, watery discharge, and congestion; antihistamines help itching and sneezing, while nasal steroid sprays control congestion better. Aim the nozzle away from the septum, breathe gently, and allow several days for substantial benefit.
Sinusitis often follows a viral infection, so routine antibiotics do not treat every episode. Saline rinses can clear mucus; use sterile, distilled, or previously boiled and cooled water. Decongestants used beyond a few days can cause rebound congestion and make blockage persist.
Chronic rhinosinusitis requires symptoms for at least 12 weeks plus objective inflammation on nasal endoscopy or CT imaging. Nasal polyps can worsen blockage and reduced smell; a deviated nasal septum causes structural, often one-sided obstruction. Chronic nasal blockage, persistent reduced smell, or repeated sinus symptoms needs examination rather than repeated self-treatment.
For most anterior nosebleeds, follow this sequence:
- Sit upright and lean forward; do not tilt your head backward, which sends blood into your throat.
- Pinch the soft part of your nose continuously for 10–15 minutes without checking early.
- Seek medical assessment if bleeding continues, blood loss is heavy, breathing is affected, or you take anticoagulants.
A nasal foreign body, especially in a child with one-sided foul discharge or bleeding, needs prompt removal by a clinician. Do not probe it with cotton buds or instruments.
When do throat, voice, swallowing, and sleep symptoms need specialist care?
A sore throat lasting beyond a short viral illness, recurring tonsillitis, or swallowing difficulty deserves assessment rather than repeated self-treatment. Viral pharyngitis does not improve with antibiotics.
Suspected group A streptococcal infection needs a rapid antigen test; children with a negative result need a follow-up throat culture, while throat swabs guide treatment rather than symptoms alone.
1. Separate throat and voice problems. Tonsillitis and acute pharyngitis can cause fever and painful swallowing; laryngitis causes hoarseness. Chronic sore throat and acid-reflux-related throat symptoms need review when they persist, recur, or occur with swallowing difficulty.
Persistent hoarseness needs laryngeal visualisation and voice assessment before antibiotics, steroids, or reflux medicine are prescribed solely for the voice.
2. Treat warning signs as prompt-care problems. Hoarseness lasting more than four weeks, neck lumps, tobacco exposure, breathing difficulty, swallowing difficulty, recent intubation, or coughing blood warrants ENT assessment. An adult neck lump lasting two weeks without clear improvement needs evaluation, often with imaging and fine-needle aspiration rather than repeated antibiotics.
3. Investigate risky snoring. Ordinary snoring becomes more concerning with witnessed breathing pauses, gasping, daytime sleepiness, resistant hypertension, or cardiometabolic disease, suggesting obstructive sleep apnoea. Home sleep-apnoea testing suits some uncomplicated adults with high suspicion; polysomnography is preferred with significant heart or lung disease, neuromuscular weakness, opioid use, stroke, severe insomnia, or another sleep disorder.
Which clinician and which ENT tests fit your symptoms?
Dental pain belongs with a dentist; skin lesions around the ear or nose belong with a dermatologist. Choose the clinician by the source of the symptom, not its location.
| Clinician | Best fit |
|---|---|
| ENT specialist | Ear, nose, throat, voice, hearing, salivary-gland disease, or persistent neck symptoms |
| ENT surgeon | Facial trauma, structural blockage, tumours, or surgery involving the face, jaws, head, and neck |
| Emergency department | Severe breathing trouble, uncontrolled bleeding, major facial trauma, or swallowed or inhaled foreign objects |
| General physician | Fever, uncomplicated infection, or symptoms needing initial assessment |
| Audiologist | Hearing tests, tinnitus assessment, and hearing-aid evaluation |
| Speech therapist | Speech, voice, language, or swallowing rehabilitation |
| Respiratory clinician | Chest symptoms, wheezing, or lower-airway disease |
| Neurologist | Neurological dizziness, imbalance, weakness, or sensory changes |
| Gastroenterologist | Reflux with persistent swallowing or upper-digestive symptoms |
| Maxillofacial surgeon | Jaw disorders, facial fractures, and complex dental or facial disease |
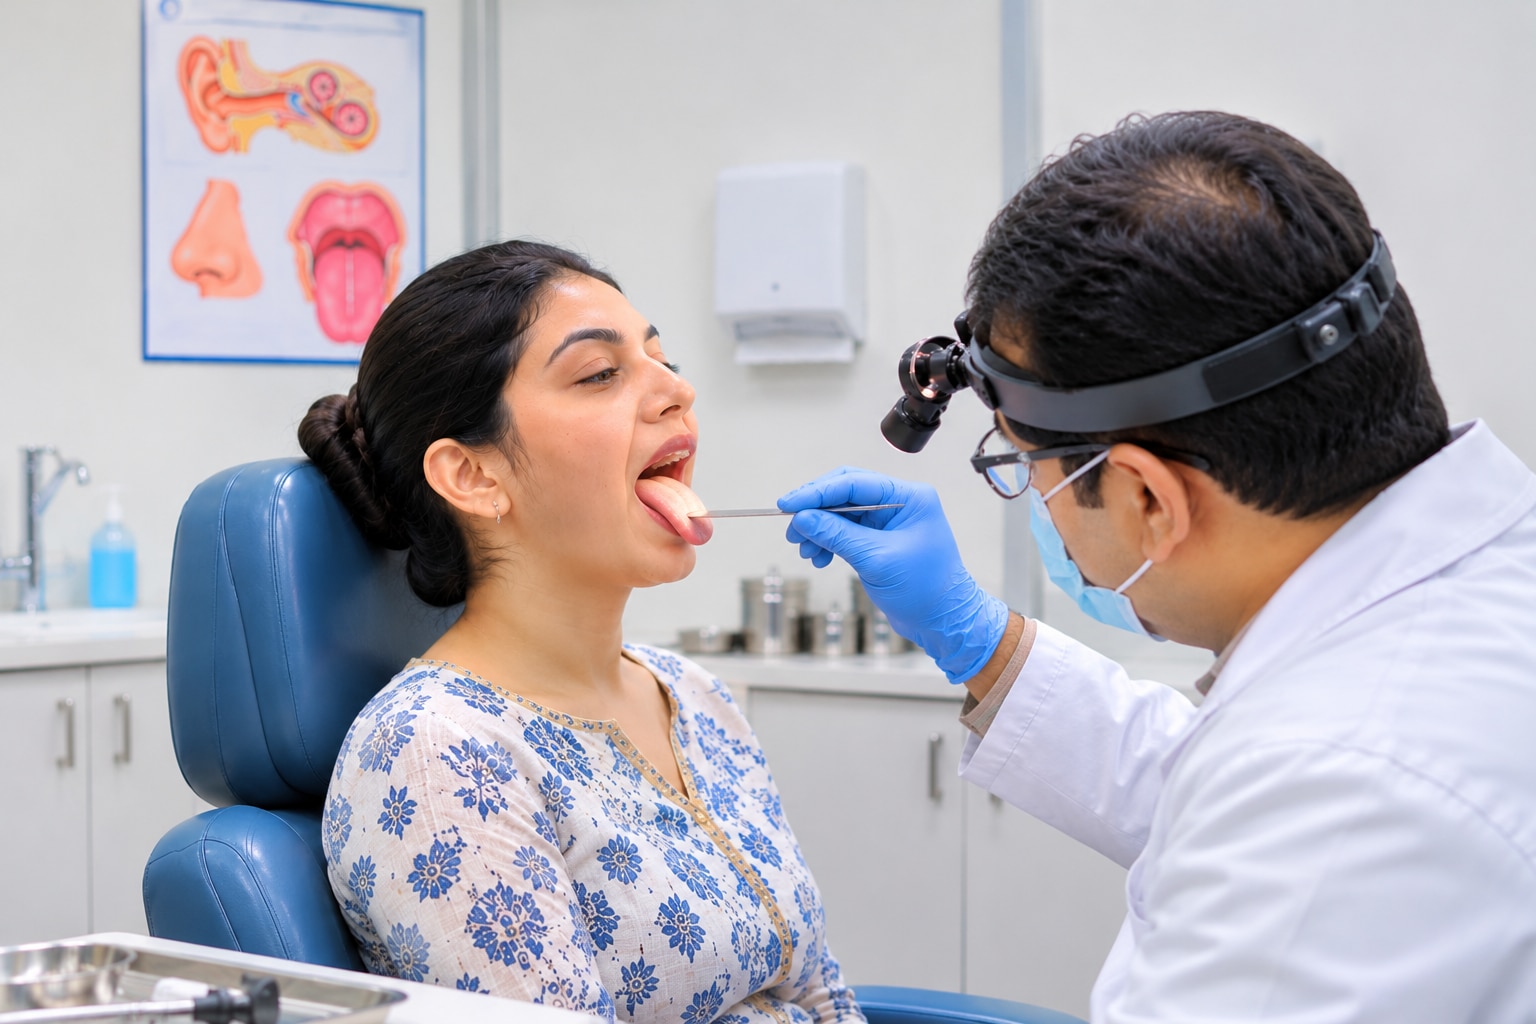
An ENT assessment may use an otoscope for otoscopy, nasal examination, throat and voice assessment, audiometry, tympanometry, nasal endoscopy, throat swabs, CT or MRI imaging, and allergy evaluation. The test must match the complaint; imaging does not replace examination.
Children need earlier review for enlarged adenoids, recurrent ear infections, mouth breathing, or speech or hearing concerns. An ENT specialist can assess adenoids, fluid behind the eardrum, and hearing before delayed speech or poor sleep becomes entrenched. A swallowed or inhaled object needs emergency assessment.
When do repeated ENT symptoms require a plan rather than another short treatment?
Do not keep repeating short courses when symptoms return. Recurrent tonsillitis, repeated sinus infections, recurrent ear discharge, persistent hoarseness, unilateral nasal blockage, one-sided hearing loss, or persistent neck lumps need a cause-based plan.
Hoarseness beyond four weeks, an adult neck lump lasting two weeks, or tobacco exposure requires examination and often laryngeal visualisation, imaging, or needle sampling rather than more antibiotics, antihistamines, ear drops, or pain medicines.
- Seek emergency assessment for sudden hearing loss within 72 hours, severe breathing difficulty, uncontrolled nosebleeding, facial or neck swelling, a swallowed or inhaled foreign body, severe infection with difficulty swallowing saliva, or rapidly worsening symptoms. For nosebleeding, sit upright, lean forward, and pinch the soft nose continuously for 10–15 minutes.
- Bring patient records showing symptom duration and triggers, fever readings, medication and antibiotic details, hearing reports, imaging, allergy history, smoking or vaping history, and an episode record.
- Ask what each next step changes: testing can take appointments and cause brief discomfort; medical treatment may require days or weeks of adherence and review; surgery involves preparation and recovery; post-procedure care adds wound, voice, ear, or nasal follow-up. Watchful waiting is appropriate only with a safety-net plan.
| Testing | Time and discomfort | Follow-up |
|---|---|---|
| Medical treatment | Days to weeks | Response review |
| Surgery | Preparation and recovery | Post-procedure care |
Patients in Hinjawadi and wider PCMC-Pune can use Hinjawadi SuperSpeciality Hospital 08048033666 for coordinated ENT, emergency, diagnostic, surgical, or inpatient evaluation.
Frequently asked questions
Which ear problems need ENT care?
Book ENT care for persistent ear pain, reduced hearing, ringing, discharge, recurrent infections, or earwax that does not clear safely. Seek urgent assessment for sudden hearing loss, severe dizziness, facial weakness, or uncontrolled bleeding.
How should common nose problems be investigated?
Persistent blockage, recurrent nosebleeds, facial pressure, reduced smell, or one-sided symptoms need clinical assessment. An ENT clinician may examine the nasal passages and select tests based on the symptoms.
When do throat, voice, swallowing, and sleep symptoms need specialist care?
Arrange specialist care for hoarseness that persists, painful or difficult swallowing, repeated throat infections, loud snoring with breathing pauses, or symptoms that disrupt sleep. Seek urgent help for severe breathing difficulty or inability to swallow.
Which ENT tests fit different symptoms?
The clinician chooses tests after examining you. Hearing symptoms may need audiometry; persistent nasal or throat symptoms may need endoscopic examination; sleep-related breathing symptoms may require a sleep assessment.
When do repeated ENT symptoms require a longer-term plan?
Ask for a management plan when symptoms recur after short treatments, affect hearing or sleep, occur on one side, or interfere with eating, speaking, work, or school. The plan should address triggers, diagnosis, treatment, and follow-up.